Pasar al contenido principal
Contacta Con Nosotros +1 210-880-3708

¿Cuando los pechos dejan de crecer?
Recuperación de la reducción de la seno: las primeras seis semanas

¿Cuando los pechos dejan de crecer? Revisado médicamente por el Dr. Michael Baumholtz, MD, FACS, cirujano plástico certificado por tabla doble · San Antonio, Texas · Reviewed October 2026 Para la mayoría de las personas, el desarrollo de la mama se completa alrededor de los 17 o 18 años, con algún cambio modesto en los primeros años. El desarrollo generalmente comienza en algún lugar entre las edades 8 y 13 [...]

¿Considerando el aumento de mama? Conoce tus opciones
Seguro de reducción de mamas Texas

¿Considerando el aumento de mama? Conoce tus opciones Escrito por Dr. Michael Baumholtz, MD, FACS, cirujano plástico certificado por tabla doble · San Antonio, Texas · Publicado octubre 2026 El aumento de la seno no es una decisión. Son seis, y la mayoría de la gente sólo sabe de dos de ellos cuando entran en una consulta. Esta página denomina a los seis, explica [...]

¿Debería combinar cirugía de mama y de vientre?

Preparación para su cirugía de la tuca Tummy: Qué tener listo para una recuperación de la madre

¿Debería combinar cirugía de mama y de vientre? Escrito por Dr. Michael Baumholtz, MD, FACS, cirujano plástico certificado por tabla doble · San Antonio, Texas · Publicado octubre 2026 La mayoría de las personas considerando ambos quieren que se hagan juntos, y a menudo esa es la llamada correcta. Lo que decide no es voluntad — es tiempo total de funcionamiento, su general [...]

¿Cuánto cuesta el aumento de mama?
Recuperación de la reducción de la seno: las primeras seis semanas

¿Cuánto cuesta el aumento de mama? Escrito por Dr. Michael Baumholtz, MD, FACS, cirujano plástico certificado por tabla doble · San Antonio, Texas · Publicado octubre 2026 Las cifras nacionales pusieron la tasa promedio del cirujano por aumento de mamas entre aproximadamente $4,575 y $8.000. Ese número no es el precio. Cubre solo al cirujano — no anestesia, la [...]

Cómo prepararse para su consulta Gynecomastia

¿Cubre TRICARE Cirugía Plástica?

Cómo prepararse para su consulta Gynecomastia Escrito por Dr. Michael Baumholtz, MD, FACS, cirujano plástico certificado por tabla doble · San Antonio, Texas · Publicado octubre 2026 Una buena consulta ginecomastia produce una respuesta clara: lo que el tejido es en realidad, lo que se puede hacer al respecto, y lo que implica. Llegar allí toma unos quince minutos [...]

baraja sin drenaje o turbera con drenajes
Fleur-de-Lis Abdominoplasty Recovery: Tips and Timeline

Tuck Tummy sin drenaje o Tummy con drenaje? Tuck Tummy sin drenaje o Tummy con drenaje? Escrito por Dr. Michael Baumholtz, MD, FACS, cirujano plástico certificado por tabla doble · San Antonio, Texas · Publicado octubre 2026 Una tuciedad sin drenaje no es una tuciedad con los desagües dejados. Es una técnica de cierre diferente [...]

¿Cuál es la mejor edad para la cirugía Gynecomastia?
Cirugía ginecológica

================================================================== ¿Cuál es la mejor edad para la cirugía Gynecomastia? Revisado médicamente por el Dr. Michael Baumholtz, MD, FACS, cirujano plástico certificado por tabla doble · San Antonio, Texas · Publicado octubre 2026 No hay una sola mejor edad para la cirugía ginecomastia. Cirujanos tiempo la operación por la condición, no el calendario: tejido que ha sido estable para [...]

Cómo dormir después de una cirugía Mami Makeover en San Antonio

- Mami maquillaje

Fecha de publicación: 4/19/2026, Autor: Dr. Michael Baumholtz Guía práctica nocturna para proteger sus resultados y recuperarse cómodamente Las primeras noches después de la cirugía a menudo traen la misma preocupación. Los pacientes están emocionados por los cambios que hicieron para sí mismos. Pueden sentir alivio de que la cirugía finalmente está detrás de ellos. Al mismo tiempo, [...]

Diferentes tipos de formas de nariz

lifting facial o lifting de cuello

Fecha de publicación: 11/9/2025, Autor: Dr. Michael Baumholtz Para hombres y mujeres, la rinoplastia no se trata de tendencias. Se trata de equilibrio – el tipo tranquilo que hace que una cara se vea armónica y natural. El Dr. Michael Baumholtz, certificado en Cirugía Plástica y Cirugía General, trata la rinoplastia como una conversación entre estructura e identidad. Él escucha primero; estudios [...]

¿Por qué son los pechos de la Copa C los más populares?
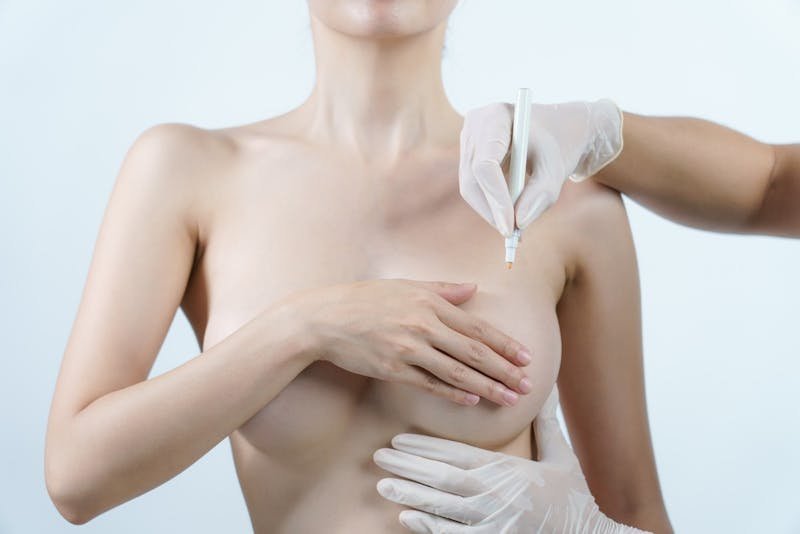
Pointy or Tube-Shaped Breasts? It Could Be Tuberous Breast Deformity Medically reviewed by Dr. Michael Baumholtz, MD, FACS, double board-certified plastic surgeon · San Antonio, Texas · Reviewed October 2026 There is a name for it. Tuberous breasts are a recognized developmental variation where the base of the breast is underdeveloped and breast tissue pushes forward into the areola, making it look full or domed. It is not a disease, and standard augmentation alone often disappoints. Key takeaways It has a name and a classification. You are not an unexplained case. The base is the problem, not the areola — the areola is being pushed. Implants alone often disappoint because the restriction stays in place. Three types, and having a different one on each side is common. First, the part that matters most Most women who have this have never heard the term. They have spent years assuming their breasts are simply unusual, that nobody else looks like this, and that there is nothing to be done. None of that is true. Tuberous breasts make up roughly ten percent of all breast malformations. There is a published classification, a known anatomical cause, and established surgical correction. Whatever you decide to do about it, you are looking at a described condition rather than a mystery. What Is Actually Different The visible features all trace back to one underlying issue: the base of the breast — the footprint where it meets the chest wall — did not develop to full width, particularly at the lower pole. Several things follow from that. What you seeWhy A pointed or tubular shape With a narrow base, the breast projects forward instead of spreading across the chest A full, domed or puffy areola Glandular tissue herniates forward through the areolar complex, creating a double contour An areola that looks too big It is enlarged relative to breast volume, and is being stretched by the tissue behind it A high breast crease The fold beneath the breast sits higher than usual A wide gap between the breasts Seen particularly where the base is narrowed in all directions Noticeable asymmetry Common — the two sides are often affected to different degrees Underneath all of it is abnormal superficial fascia, which forms adhesions between the skin and the deeper layers and physically restricts the base from widening. That detail matters enormously for treatment, as the next section explains. The Three Types The commonly used classification sorts tuberous breasts into three types, and the type tells you a good deal about what correction would involve. Type I — about 56% of cases Underdevelopment of the lower inner quadrant only. The areola is displaced downward and inward. The breast is usually of normal volume, so correction here is more about shape than size. Type II — about 26% of cases Both lower segments are deficient, with the areola displaced downward. Around 74% of type II breasts have insufficient volume and need an implant as part of correction. Type III — about 18% of cases Both upper and lower segments are involved. The base is narrowed in all directions, giving a distinctly tubercle-like shape with a wide gap between the breasts. All type III breasts have insufficient volume and need an implant. Different types on each side is normal. If one breast looks noticeably different from the other, that is characteristic of the condition rather than a sign that something else is going on. Why Implants Alone Often Disappoint This is the most useful thing on this page if you are considering surgery, and it is where tuberous breasts differ fundamentally from a straightforward augmentation. The restriction has to be released The lower segment of a tuberous breast is inelastic, held in place by tight fascial adhesions. Put an implant behind it without dealing with those adhesions and the lower breast stays under-filled — the implant fills what it can and the constriction holds the rest. Worse, the pressure of the implant pushing against that inelastic tissue can force the areola forward again, recreating the protrusion you were trying to correct. So a surgeon treating this as "a small breast that needs an implant" is treating the wrong problem. The volume deficit is real in types II and III, but the restriction is what gives the breast its shape, and volume alone does not undo it. This is the single most important question to establish at a consultation: does the surgeon recognize this as tuberous, and what are they planning to do about the constriction specifically? Double Bubble: The Complication to Understand Correcting a tuberous breast usually involves lowering the breast crease, and that creates a specific risk worth knowing by name. A double bubble is a visible second crease running across the breast after surgery. It comes in two forms: Immediate. Caused by a mismatch in skin thickness between the original breast skin and the chest skin recruited when the crease is lowered. Later, sometimes called waterfall deformity. Caused by skin relaxing and breast tissue descending over the implant with time. A pinch test of the breast and chest skin before surgery can help predict the risk. If a surgeon has not mentioned double bubble when discussing tuberous correction with you, it is worth raising. How Correction Works One published technique approaches it this way: An incision at the upper edge of the areola. Dividing the deep surface of the restrictive fascial layer along a newly positioned breast crease — this is the step that releases the constriction. Preserving the lower segment glandular tissue rather than removing it, so there is something to fill the newly released lower breast. Placing the implant above or below the chest muscle, chosen by a pinch test — above or below two centimeters of tissue cover. Other approaches exist, including staged operations and tissue expansion for more severe cases. Techniques using an incision at the lower areolar edge have been described as sometimes providing insufficient tissue to fill the lower breast. What matters is less which specific technique and more that the plan addresses the restriction, the volume and the areola rather than only one of the three. What the Published Results Show One series reported on fourteen tuberous breasts in nine women, average age twenty-two, followed for an average of three years. The authors reported no early or late complications, no tissue loss, no double bubble, and well-shaped lower breasts, with satisfaction described as high. Read that with the sample size firmly in mind. Nine women is a very small series. Zero complications in nine patients is not evidence that a technique is complication-free — with numbers that small, zero is a result you would often get by chance even from a procedure that does carry real risk. It was also a single center with no comparison group, and satisfaction was described rather than measured with a validated instrument. Encouraging, in other words, and nowhere near conclusive. The practical version: ask any surgeon how many tuberous corrections they have personally performed, and ask to see their own results. If You Are Still Developing Tuberous breasts usually become apparent as the breasts develop, which means many people first notice it as teenagers. Surgical planning should wait until breast development is complete. Operating on a breast that is still changing risks a result that no longer fits you a few years later. If you are under eighteen, this is a conversation to have with a parent or guardian and a physician, and there is no reason to hurry it. Knowing what the condition is called, though, is useful at any age — and for a lot of people, that is the part that actually helps. More on breast development and when it finishes: when do breasts stop growing. What to Ask at a Consultation Useful questions Do you think I have tuberous breasts, and which type on each side? What specifically will you do about the constriction? Not just the volume. Where will my breast crease end up, and what is my double bubble risk? Do I need an implant, or is this mainly a shape correction? What will happen to my areola? How many tuberous corrections have you done? Would you do this in one operation or two, and why? How different will my two sides look afterward? If any of this sounds like your breasts, the useful next step is simply finding out. Identifying which type you have, on each side, is what turns a vague dissatisfaction into a specific and answerable question. Dr. Michael Baumholtz is double board-certified in plastic surgery and general surgery, with more than two decades of experience in San Antonio. Virtual consultation · Request an appointment Frequently Asked Questions Why do my breasts look pointy or tube-shaped? It may be tuberous breasts, a recognized developmental variation in which the base of the breast is underdeveloped, particularly at the lower pole. Because the base is narrow, the breast projects forward rather than spreading across the chest, which produces a pointed or tubular shape rather than a rounded one. What are tuberous breasts? A developmental difference in how the breast base forms. Abnormal fascia creates adhesions that restrict the base from widening, the crease beneath the breast often sits higher than usual, and breast tissue herniates forward into the areola. They account for roughly ten percent of all breast malformations. Why does my areola look puffy or domed? Because glandular tissue is pushing forward into it. In tuberous breasts the tissue herniates through the areolar complex, which creates a double-contour appearance and makes the areola look enlarged relative to the size of the breast. The areola is not the problem itself; it is being stretched by what sits behind it. Are tuberous breasts dangerous? No. It is a variation in how the breast developed rather than a disease, and it does not threaten your health. The reasons people seek correction are appearance and the distress that can come with it, not medical risk. That said, any new lump or change should be assessed by a doctor as it would be for anyone. What are the types of tuberous breasts? Three, in the commonly used classification. Type I, about 56 percent of cases, involves the lower inner quadrant only, with the breast usually of normal volume. Type II, about 26 percent, involves both lower segments. Type III, about 18 percent, involves upper and lower segments with the base narrowed in all directions. Having different types on each side is common. Will breast implants alone fix tuberous breasts? Often not satisfactorily. The lower segment of a tuberous breast is inelastic and held by tight fascial adhesions, so an implant placed without releasing those restrictions tends to leave the lower breast under-filled. The pressure of the implant against inelastic tissue can also push the areola forward again, recreating the protrusion. What is a double bubble deformity? A visible second crease across the breast after augmentation, and the main complication to understand with this condition. The immediate form arises from a mismatch in skin thickness when the breast crease is lowered. A later form, sometimes called waterfall deformity, happens when skin relaxes and breast tissue descends over the implant. How are tuberous breasts corrected? By addressing the restriction rather than only adding volume. The technique described in one published series uses an incision at the upper edge of the areola, divides the restrictive fascial layer along a newly positioned breast crease, preserves the lower segment tissue, and places an implant above or below the muscle depending on how much tissue covers it. Do I need an implant to correct tuberous breasts? It depends on the type. In type I the breast is usually of normal volume, so correction may focus on shape rather than size. In type II, around 74 percent have insufficient volume and need an implant, and in type III all do. Which applies to you is established by examination. Can I breastfeed with tuberous breasts? Many women can, though some have reduced glandular tissue and find milk supply is affected. This varies considerably between individuals and is not something a web page can predict for you. If you are planning a family, raise it with your obstetric provider or a lactation consultant, and mention it to your surgeon before any procedure. Should I have surgery while I am still a teenager? Breast development should be complete before surgical planning, because operating on a breast that is still changing risks a result that stops matching you. For anyone under eighteen this is a conversation involving a parent or guardian and a physician, and there is no reason to rush it. Learning what the condition is called is useful at any age. How well does correction work? One published series of fourteen tuberous breasts in nine women reported no early or late complications and well-shaped lower breasts at an average of three years follow-up. Nine patients is a very small sample, so that result is encouraging rather than conclusive. Ask any surgeon how many of these they have performed and what their own results look like. The Short Answer Pointy or tube-shaped breasts with a full, domed areola often mean tuberous breasts — a developmental variation where the breast base never widened properly and tissue herniates forward into the areola. It is not a disease, it is described and classified, and roughly one in ten breast malformations are this. The thing to know before surgery is that implants alone frequently disappoint, because the restriction that shaped the breast is still there afterward. Releasing it is the operation. Adding volume is only part of it. Source Correction of tuberous breast deformity — classification and surgical series This article is general information and does not replace assessment by a qualified surgeon. Outcome figures come from a series of nine patients and should be read as indicative rather than as expected rates. Questions about breastfeeding should be directed to your own obstetric provider. Last reviewed October 2026.

Fecha de publicación: 1/8/2026, Autor: El Dr. Michael Baumholtz El Dr. Michael Baumholtz lo escucha cada semana. Alguien camina pidiendo una carta específica, a menudo vinculada al resultado de un amigo o un post en línea. Él escucha, y luego redefine la conversación. En su práctica, el tamaño de la taza no es el plan y no es el objetivo. Es [...]

Saltar al contenido
EspañolesEspañolEspañol
Contacta Con Nosotros